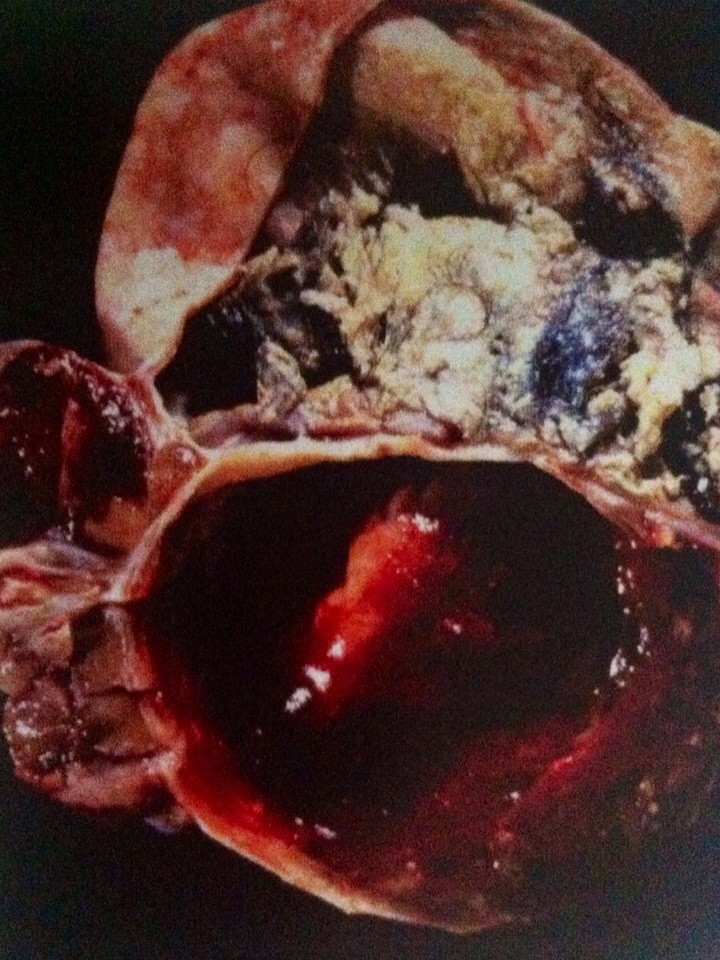
- These tumors grossly may resemble typical leiomyomas but often have a fleshier, soft, yellow or brown sectioned surface, sometimes with hemorrhage and/or necrosis. They may be less well circumscribed than typical leiomyomas.
- Cellular leimyomas are defined as leiomyomas that are 'significantly' more cellular than the normal myometrium but which are otherwise typical.
- Highly cellular leimyomas (HCL) are characterized by a cellularity similar to that of an endometrial stromal tumor (EST), and may be misdiahnosed as an endometrial stromal nodule when well circumscribed.
- Features that facilitate the distinction of HCLs from an EST and include a fascicular growth pattern, spindle-shaped tumor cells, blood vessels with thick muscular walls, cleft-like spaces, and immunoreactivity for desmin and h-caldesmon. About 40% of HCLs are CD10 positive, but CD10- negativity favors HCL over an EST.
- Recently described markers that are expressed in smooth muscle tumors but not stromal tumors that may also aid this differantial are indicated elsewhere.
- The differantial of CLs also includes focal hypercellularity of the myometrium. This finding is more common in postmenopausal women and tends to involve superficial myometrium immediately subjacent to the endometrium. The absence of a mass, the sometimes band-like arrangement, and merging with normal myometrium facilitate the diagnosis.

CLİNİCAL FEATURES AND BEHAVİOR
- This tumor is the least common variant of ovarian carcinoid. Bases on the only series of such cases (Baker et al.), the age range has varied frıom 14 to 74 years and the clinical presentation is nonspecific.
- Most ofthe reported tumors have been clinically benign, except for several tumors with a carcinomatous component (see below) that had extraovarian spread at presentation and a fatal course.
PATHOLOGİCAL FEATURES
- The tumors, which range up to 30 cm in diameter, may be entirely solid but more commonly form a mural mass in a mature cystic teratoma or other type of cystic ovarian tumor (mucinous borderline tumor or carcinoma, borderline Brenner tumor, epidermoid cyst). Two tumors were intimately admixed with yolk sac tumor.
- Mucinous carcinoids can be divided into there categories based on their microscopic appearance:
- 'Well-differentiated' tumors are composed of small glands, sometimes lying within pools of mucin, lined by goblet cells and differentiation. The cells show minimal atypia.
- 'Atypical' tumors contain crowded to confluent glands, small islands with a cribriform pattern, and scattered microcystic glands, with cells similar to those in the well-differentiated tumors and mild to moderate atypia.
- 'Carcinoma arising in mucinous carcinoid' are camposed of solid nests or closely packed glands composed of mucin-poor cells that are markedly atypical and mitotic. Signet-ring cells are also usually prominent. Foct of well-differentiated or atypical carcinoid are typically present.
- The tumor cells are variably immunoreactive for synaptophysin and chromogranin. One or more intestinal-type polypeptide hormones have also been found in some tumors.
- Other elements present in some tumors have been noted above. Additionally, occasional tumors have contained a component of insular, trabecular, or strumal carcinoid.

- Nodular aggregates of histiocytes resembling Langerhans'/interdigitating cells can occur in the endometrium. The examples described by Kim et al. were an incidental microscopic finding in curettage specimens in women of reproductive age. The nodules were solitary and 0.3-1.5 cm in maximum.
- The histocytes are round to polygonal with distinct cytoplasmic borders and moderate amounts of pale amphophilic or eosinophilic granular cytoplasm. Small cytoplasmic vacuoles, but not cytoplasmic lipid or pigment, may be present. The avoid to reniform nuclei have occasional grooves, fine chromatin, and inconspicuous nucleoli. Mitoses were frequent in one case.
- The cells are immunoreactive for CD68 and lysozym but negative for S100 and cytokeratin.
- Uterine involment by Langerhans' cell histocytosis can be excluded by the absence of eosinophils as well as negative staining for S100. The distinctive apperance of the histiocytes, their nodular arrangement, and the absence of lipid and/or pigment xanthogranulomatous endometritis.
Struma Ovarii
- The term 'struma' is reserved for cases in which thyroid tissue is the predominant or sole component or forms a grossly recorgnizable tumor in a teratoma.
- The peak frequency is in the fifth decade, but occasional cases occur much earlier or later. When clinically significant (many are incidental findingsin a resected dermoid), the presentation is similar to that of any ovarian mass. In rare cases, however, there is clinical evidence of hyperthroidism.
- Ascites is present in as many as a third of cases, and occasionally is accompanied by Meigs' syndrome. The association of a pelvic mass, ascites, and an elevated serum level of CA-125 can mimic ovarian cancer.

- Lehman and Hart have describe localized papillary endometrial proliferations that could lead to a misdiagnosis of a villoglandular endometrioid adenocarcinoma,especially in a fragmented biopsy or curettage specimen.
- The lesions typically occur in postmenopausal women who present with bleeding. Two-thirds of the lesions involved polyps, but in some cases the lesion occured in the absence of, or at a distance from, a polyp.
- The proliferations are characterized by papillae with fibrovascular cores and variable degrees of branching. The papillae are covered by epithelial cells with bland to mildly atypical nuclei, with occasional mitotic figures in some cases.
- One or more metaplastic epithelial changes are often present, including (in descending order of frequency in the cited study) mucinous, eosinophilic cell, ciliated cell, squamous, and hobnail cell metaplasia.
- The patients had uneventful outcomes, but only three who were not treated by hysterectomy had appreciable follow-up.
- Awareness that the lesion tend to occur in polyps, the typically bland cytologic features, and the usual presence of metaplastic epithelia facilitate the diagnosis.

- Endometrial polyps are typically encountered in the reproductive and postmenopausal age groups;65% of patients are over the age of 40. Polyps are present in as many as 25% of endometrial biopsy specimens performed for abnormal uterina bleeding, although they are often an incidental finding. Sbouth 10%of polyps prolapse into the endocervix, often mimicking an endocervical polyp.
- Polyps are the most common endometrial lesion associated with tamoxifen therapy, being present in as many as one-third of these patients. Tamoxifen-related polyps tend to be larger, more commonly multiple, and are more likely to recur.
- Polyps most often arise in the fundus. In a study of 1100 polyps, Peterson and Novak found them to range from 0.3 to 12 cm (mean, 2.3 cm); 20% werw multiple. Polyps have a broad to narrow base, a usually smooth external surface, and an often cystic and/or fibrotic sectioned surface. Focal hemorrhage may be seen, particularly at their tips, due to torsion with subsequent infaretion.
Microscopic features
- The glandular and stromal morphology is highly variable and may differ from or reflect the appearance elsewhere in the endometrium.
- The glands are often inactiveand cystic, particularly after the menopause, but functional (proliferative or secretory), metaplastic, hyperplastic, or even carcinomatous glands may be present. The glands are often arranged parallel to the surface epithelium. We allow some gland crowding in polyps, including cellular stratification and mitotic activity, withouth rendering a diagnosis of hyperplasia.
- A mixture of endometrial and endocervical-type glands may be ancountered in polyps arising near the internal os.
- Glandular features more commonly present in tamoxifen-related than in tamoxifen-unrelated polyps includeglands polarized along the long axis of the polyps, focal stromal hypercellularity, staghorn-shaped glands, small glands, and metaplastic glands.
- Polyps may contain a distinctive proliferation of fibrous-cored papillae and metaplastic epithelium, as described by Lehman and Hart (see below).
- Hyperplasia and adenocarcinoma have been found in as many as 11-30% and 0.5-3% of polyps, respectively, in the general population. Carcinoma has been found in 3.0- 10.7% of polyps in tamoxifen-treated women.
- İn women with complex hyperplasia within polyps, da Costa and Mittal found hyperplasia or adenocarcinoma of nonpolypoid endometrium in the hysterectomy specimen in 72% and 31% of cases, respectvely. Some of the carcinomas were myoinvasive.
- Carcinomas found in polyps (tamoxifen related and tamoxifen unrelated) may be confined to the polyp or be part of a multifocal endometrial neoplasia. They are usually endometrioid or serıous, or rarely other cell types. The serous carcinomas, in particular, are often microscopic and /or noninvasive and can be overlooked. Tmoxifen-related polyps may also harbor metastatic lobular breast carcinoma.


- The stroma of endometrial polyps may be fibrotic and sparsely cellular, especially in tamoxifen-related polyps. İn other cases, it resembles normal or hypercellular endometrial stroma; in these polyps, mitotic figures in the stromal cells may be present.
- Blood vessels, which are often thick-walled and/or hyalinized, are more numerous in polyps than in the normal endometrium, and are sometimes a helpful clue to the diagnosis.
- Atypical stromal cells, which may be multinucleated, are a rare focal, multifocal, or diffuse finding within a polyp. Their nuclei can be moderately to severely atypical and hyperchromatic, often with a smudged appearnce. Mitotic figures are usually absent.
- Other uncommon stromal findings include foci of smooth muscle and decidua, the latter usually reflecting exogenous progestin use latter usually reflecting exogenous progestin use or pregnancy.
- Vascular thrombosis and hemorrhagic necrosis can occur within the polyp, and hemorrhagic necrosis can occur within the polyp, and may result in reactive atypia of the epithelium or stroma of the polyp.

- This is an uncammon distinctive soft tissue tumor that in females most commonly arises in the vulva rare tumors have arisen in the vagina, parineum, inguinal region, or urethra.
- The patents are of peproductive or postmenopausal age (mean,46 years) and present with a superficial mass. The tumors are successfully treated by local excision; one recurred locally.
- In the largest series, the tumors measured 0.6-12 (median 2.8) cm and were usually well circumscribed, with a solid, white, tan, or grey sectioned surface.
- Microscopic examnation reveals a cellular proliferation of spindle cells arranged in short interesting fascicles, numerous small to medium-sized, thick-walled, often hyalinized, blood vessels, and short wispy collagen bundles. The spindle cells have scanty eosinophilic cytoplasm and bland nuclei. Mitotic figures are usually uncommon.
- Fat is present in about 25& of cases, but usually accounts for less than 5% of the tumor. Hypocellular areas related to areas of edema, myxoid change, or hyalinization may be present.
- Unusual to rare findings include an infiltrative border, absence of thick-walled vessels, dilated hemangiopericytomatous vessels, vague nuclear palisading, mild cytologic atypia, multinucleated cells (like those in symplastic leiomyomas), frequent mitotic figures (up to 11 MFs/10 HPFs), and stromal lymphoid aggregates.
- The spindle cells are immunoreactive for vimentin, CD34, smooth muscle actin, and desmin in approximately 100%, 50%, 20&, and 10% of caces, respectively, Nuclear staining for ER, PR, or both is present in about half the caces. Staining for keratin, EMA, and S100 protein is negative.